
Medical Retina

Protect the part of the eye that turns light into sight.

Consultant retina assessment for diabetes-related eye disease, macular conditions, retinal vascular disease, tears, haemorrhage and premature infants—supported by imaging, laser and injection-based care when indicated.

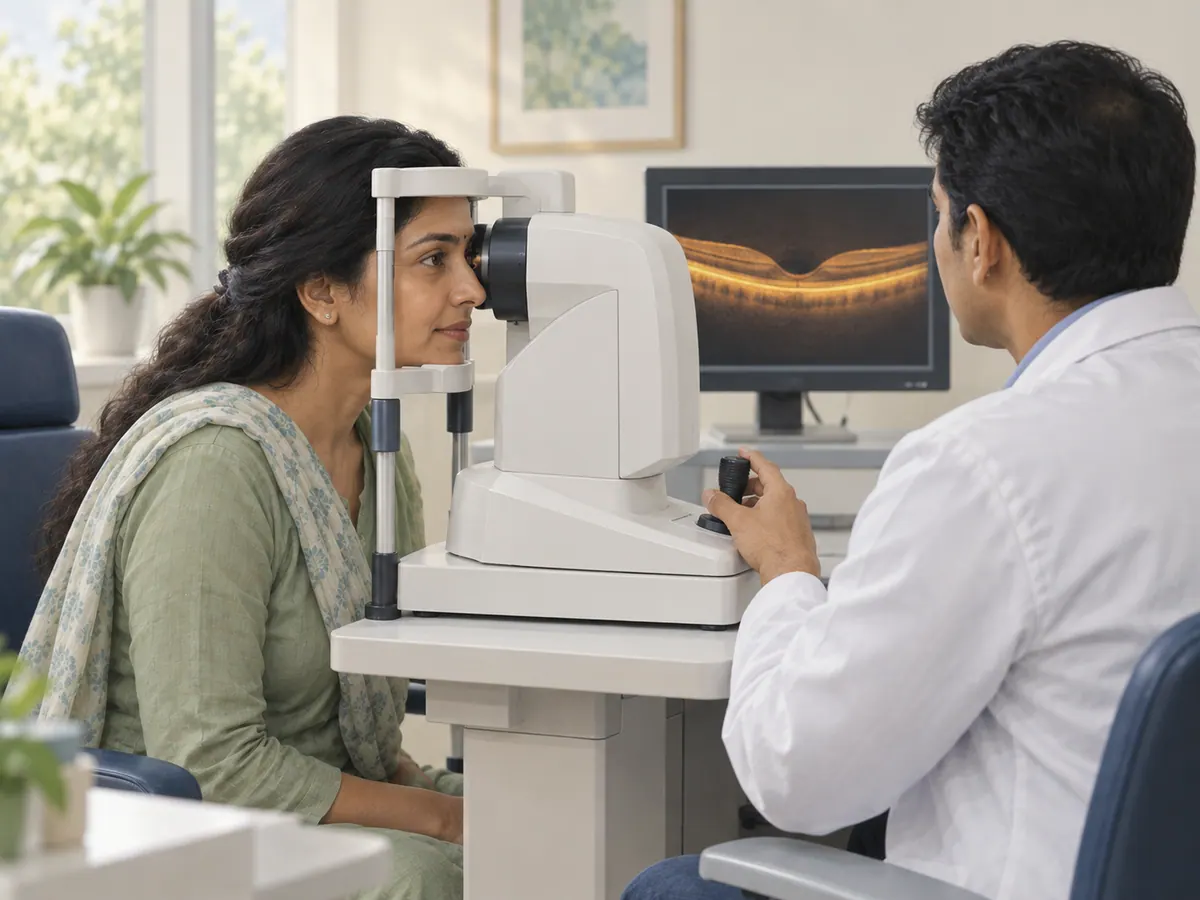
Illustration of a patient having a retinal imaging examination
Every Thursday Nallasopara East
Understanding the retina

The retina receives the image. The macula supplies the detail.

The retina is a thin layer of light-sensitive nerve tissue lining the inside of the back of the eye. It changes focused light into electrical signals that travel through the optic nerve to the brain, where they are interpreted as vision.

The macula is the specialised central part of the retina used for reading, recognising faces, colour vision and fine detail. The peripheral retina supports side vision and helps detect movement. Damage in either area can matter, but macular disease is especially likely to affect central visual tasks.

Urgent retinal symptoms

Some retina problems are painless—and should not wait for Thursday.

A retinal tear, detachment, vascular blockage or severe inflammation can change vision suddenly without causing eye pain. If symptoms are new, sudden or rapidly worsening, seek prompt eye assessment or an appropriate emergency service.

  • A sudden shower or marked increase in floaters
  • Flashes of light that are new or increasing
  • A dark curtain, shadow or missing area of vision
  • Sudden painless loss or severe reduction of vision
  • New distortion—straight lines appearing bent or wavy
  • Rapidly worsening vision after an eye injection or procedure
Retinal conditions

Different diseases can produce similar blur—but require different treatment.

Dilated examination and imaging help identify whether the problem is leakage, blocked circulation, abnormal vessels, a tear, bleeding, traction or degeneration. Treatment is chosen for the underlying cause rather than the symptom alone.

01Diabetes-related retina disease

Diabetic retinopathy

Diabetes can damage and close the retina’s smallest blood vessels. Early disease may have no symptoms; later stages can cause leakage, macular swelling, abnormal new vessels, bleeding or traction on the retina.

How care may be planned

Care may include closer monitoring, control of diabetes and blood pressure, OCT imaging, intravitreal injections, retinal laser or vitreoretinal surgical referral depending on the stage.
02Central retinal swelling

Diabetic macular oedema

Diabetic macular oedema occurs when damaged retinal vessels leak fluid into the macula—the area responsible for detailed central vision. It may blur or distort reading and face recognition.

How care may be planned

OCT helps measure the swelling and monitor response. Anti-VEGF injections are commonly considered, while laser or other treatment may be appropriate in selected situations.

03Dry and wet AMD

Age-related macular degeneration

AMD affects the macula and can blur, distort or remove parts of central vision while side vision is often retained. Dry AMD usually progresses more slowly; wet AMD involves abnormal leaking or bleeding vessels and needs timely assessment.

How care may be planned

Monitoring, home-vision advice and risk reduction may be used for dry AMD. AREDS2 supplements help only certain stages and should be recommended after examination. Wet AMD is commonly treated with repeated anti-VEGF injections.

04BRVO and CRVO

Retinal vein occlusion

A blocked retinal vein can cause sudden, usually painless blur or loss of vision. Branch occlusion affects part of the retinal circulation; central occlusion affects the main retinal vein and can be more extensive.

How care may be planned

OCT and retinal examination assess macular oedema and complications. Treatment may include anti-VEGF injections, selected laser treatment and attention to blood pressure, diabetes, glaucoma or other vascular risks.

05Time-sensitive peripheral retina disease

Retinal tears and detachment

A retinal tear may allow fluid to pass underneath the retina and cause a detachment. Sudden flashes, many new floaters or a curtain-like shadow can be warning symptoms even when there is no pain.

How care may be planned

Suitable tears may be sealed with laser retinopexy before detachment develops. A retinal detachment usually needs urgent evaluation and often vitreoretinal surgery rather than routine clinic treatment.

06Bleeding into the eye’s clear gel

Vitreous haemorrhage

Blood leaking into the vitreous can cause spots, cobwebs, haze or marked painless loss of vision. Common causes include proliferative diabetic retinopathy, a retinal tear or other abnormal retinal vessels.

How care may be planned

The priority is to identify the cause and check whether the retina is attached. Ultrasound may be needed when blood blocks the view; treatment can include observation, laser, injections or surgical referral.

07ROP in premature infants

Retinopathy of prematurity

ROP is abnormal retinal blood-vessel development in premature or very low-birth-weight babies. Parents cannot see its early stages, so examinations must follow the neonatal team’s timing even when the baby appears well.

How care may be planned

Many mild cases are monitored, while higher-risk disease may need laser, anti-VEGF treatment or surgery. Follow-up timing is critical because ROP can progress quickly and may recur after treatment.

Diabetes and the retina

Do not wait for blur before arranging a diabetic retina check.

Diabetic retinopathy can be present while vision still feels normal. A comprehensive dilated examination can identify microaneurysms, bleeding, leakage, reduced circulation or abnormal new vessels before the patient notices a major change.

Most people with diabetes need a dilated eye examination at least annually, but the interval should be personalised. Existing retinopathy, pregnancy, rapid changes in diabetes control or other eye findings may require closer review.

Bring to your appointment
  • Recent HbA1c or diabetes reports, if available
  • A current medicine and eye-drop list
  • Previous OCT scans, injection dates or laser records
  • Your spectacles and any recent vision prescription
Book diabetic retina screening
Retina diagnostics

See the surface, layers, circulation and hidden structures.

Not every patient needs every test. The retina specialist selects imaging based on the suspected condition and whether the result is likely to change monitoring or treatment.

Illustration of an OCT-style retinal layer scan and retinal circulation map
01

Dilated retinal examination

Dilating drops widen the pupil so the macula, optic disc and peripheral retina can be examined with slit-lamp lenses and indirect ophthalmoscopy. Vision may remain blurred and light-sensitive for several hours.

OCT

Optical coherence tomography

OCT uses reflected light to create cross-sectional images of retinal layers. It helps detect and measure macular oedema, fluid, traction and structural changes, and is often repeated to monitor treatment response.

FFA

Fundus fluorescein angiography

FFA photographs retinal circulation after fluorescent dye is injected into a vein. It can map leakage, blocked circulation and abnormal vessels when the result is likely to change diagnosis or treatment planning.

04

Retinal photography and ultrasound

Fundus photographs document visible retinal findings over time. If cataract or vitreous haemorrhage blocks the view, an ocular ultrasound may help assess the retina and vitreous behind the opacity.

Treatment approaches

The aim may be to improve vision, stabilise it or prevent further loss.

Retinal treatment often depends on repeated measurements and response over time. The expected benefit, number of visits, possible risks and signs requiring urgent contact should be discussed before a procedure.

01

Observation and risk-factor control

Not every retinal finding needs immediate procedure-based treatment. Scheduled imaging and examinations may be combined with diabetes, blood-pressure, lipid and smoking-risk management through the patient’s physicians.

02

Intravitreal injections

Anti-VEGF medicines and, in selected conditions, steroid medicines are injected into the vitreous after numbing and antiseptic preparation. Many retinal diseases need a planned series rather than a single injection.

03

Retinal laser

Laser can seal selected retinal tears, treat areas of abnormal or non-perfused retina and reduce the risk from proliferative diabetic retinopathy. The purpose and possible effects differ by laser pattern.

04

Vitreoretinal surgical referral

Retinal detachment, non-clearing vitreous haemorrhage, traction or other surgical disease may need vitrectomy or another operation. The retina clinic can assess urgency and coordinate referral when surgery is indicated.

Availability and suitability of injections, laser and surgery depend on the diagnosis, examination, medicine selected, procedure setting and specialist recommendation. Some surgical conditions require referral to a vitreoretinal surgical centre.

Premature infant retina care

ROP screening follows the baby’s neonatal timeline—not visible symptoms.

Babies born very prematurely or at very low birth weight can develop abnormal retinal vessels without any outward sign. The neonatal or paediatric team determines whether screening is required and when the first examination should occur.

Follow-up dates must be kept precisely because the retina may change quickly. Mild disease may only need observation, while higher-risk ROP can require laser, anti-VEGF treatment or surgery under an appropriately trained team.

Your Thursday visit

Plan for dilation, review and a decision you can understand.

01

History and vision

Symptoms, timing, medical conditions, medicines and prior retina treatment are reviewed before vision and eye pressure are checked.

02

Dilated examination and imaging

Drops widen the pupil for a detailed retina examination. OCT, photography, FFA or ultrasound is arranged only when indicated.

03

Monitoring or treatment plan

The specialist explains the diagnosis, urgency, treatment choices, follow-up interval and whether laser, injection or surgical referral is appropriate.

Dilation can blur near vision and increase light sensitivity for several hours. Consider bringing sunglasses and avoid driving until vision is safe.

Insurance and cashless guidance

Retina coverage often differs between consultation, imaging and procedures.

Outpatient OCT or FFA may not be covered even when laser, injections or surgery are eligible. Some policies require pre-authorisation, a confirmed diagnosis, previous treatment records and limits linked to the medicine or procedure package.

JEWCC can help prepare available clinical documents, but approval and reimbursement decisions remain with the insurer or TPA.

Thursday retina clinic

Nallasopara East—near the railway station.

The retina clinic is held at the Nallasopara East eye centre every Thursday. Call before travelling to confirm the appointment time, planned dilation and whether old scans or reports should be brought.

Retina FAQs

Useful details before the Thursday clinic.

01When is the retina specialist available?

The consulting retina specialist is available every Thursday at the JEWCC Nallasopara East centre. Call before travelling to confirm the current appointment time and whether dilation or a specific test is likely to be needed.

02Do retinal problems always cause symptoms?

No. Diabetic retinopathy and several other retinal conditions may begin without noticeable symptoms. A dilated retinal examination can detect changes before vision is affected.

03How should a person with diabetes prepare for retina screening?

Bring recent diabetes reports if available, a medicine list, current spectacles and previous eye scans or injection records. Most people with diabetes need a dilated retinal examination at least annually, but the interval can be shorter during pregnancy or when retinopathy is already present.

04What is the difference between OCT and FFA?

OCT is a non-contact light scan that shows cross-sections of retinal layers and fluid. FFA uses fluorescent dye injected into a vein and a sequence of retinal photographs to map circulation, leakage and blocked areas. The specialist chooses the test based on the clinical question.

05Are eye injections always a one-time treatment?

Often not. Anti-VEGF treatment for diabetic macular oedema, wet AMD or vein-occlusion-related swelling commonly requires a planned loading phase and continued monitoring. The number and spacing of injections depend on response and the condition being treated.

06Does every retinal tear need surgery?

A suitable retinal tear may be treated with laser retinopexy. If the retina has detached, an operation is often required and timing can be urgent. The correct treatment depends on the tear, symptoms, vitreous traction and whether fluid has passed under the retina.

07Are retina tests, laser or injections covered by insurance?

Coverage differs by policy. Outpatient consultations and scans may be excluded even when a procedure is covered. Injections, laser or surgery may require pre-authorisation, diagnosis documents and limits for the medicine or package. The insurer or TPA makes the final decision.